 EN

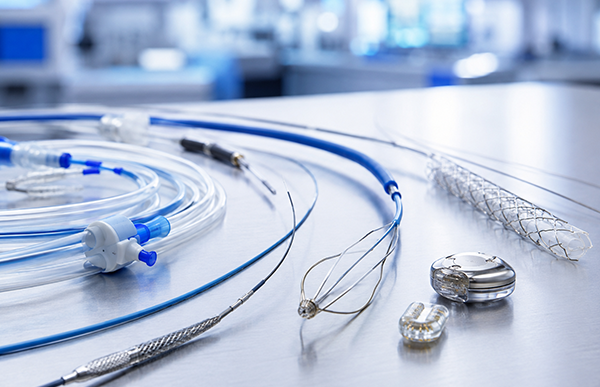
Blood-contacting devices face a difficult design problem: the material must perform its mechanical job while interacting with a highly reactive biological environment. Once blood reaches a foreign surface, proteins begin to adsorb, platelets can attach, and coagulation pathways may be activated. For catheters, vascular implants, extracorporeal circuits, and stents, surface treatment can therefore become part of the device’s overall thrombosis-control strategy.
An anti thrombogenic coating is intended to reduce the surface events that contribute to clot formation. Two well-known approaches are phosphorylcholine (PC) and heparin. They share the same broad goal—improving blood-facing performance—but they do not work in the same way.
Phosphorylcholine is a zwitterionic group associated with the outer surface chemistry of cell membranes. When incorporated into a coating, PC can create a highly hydrated interface that makes nonspecific protein adsorption less favorable. Lower protein deposition can, in turn, reduce opportunities for platelet adhesion and activation.
This is a surface-engineering approach rather than a drug-eluting anticoagulant mechanism. It can be relevant for devices where manufacturers want a non-heparin route to improving blood compatibility. SILVERMARS® uses MPC-polymer chemistry in its phosphorylcholine product family, with formulations intended for different substrates, device structures, and implantation scenarios.
For devices such as vascular implants, a PC-based stent coating can be evaluated as one option when surface hemocompatibility and resistance to nonspecific biological adhesion are important design objectives.
Heparin coatings follow a different principle. Heparin is an anticoagulant, and immobilizing it on a device surface is intended to provide localized anticoagulant activity where blood contacts the material. This strategy has been used in extracorporeal circulation and other blood-contacting systems for many years.
Clinical and experimental literature suggests that the choice between PC and heparin should not be reduced to a simple “better or worse” comparison. Device geometry, duration of blood contact, flow conditions, substrate, sterilization method, coating stability, and the intended clinical use all influence which strategy is appropriate. Reviews of anti-thrombogenic coatings also show that multiple surface technologies are being investigated rather than a single universal solution. [1–3]
The phrase blood contact safe coating is useful in commercial searches, but it should not be treated as a standalone regulatory claim. A coating may be designed to improve blood compatibility, yet the finished medical device still requires device-specific biological evaluation, performance testing, and risk assessment.
For engineers, the practical questions are more specific: Does the coating remain intact after manufacturing and sterilization? Does it perform on the final device geometry? Does it maintain its intended surface function after simulated use? And are the test methods relevant to the duration and type of blood contact?
PC can be attractive when a biomimetic, non-heparin surface modification is preferred. Heparin may be appropriate when an anticoagulant-based surface mechanism fits the device and clinical strategy. Neither option removes the need for validation on the finished product.
The strongest coating decision is therefore not based on a single material label. It comes from matching surface chemistry to device requirements, manufacturing constraints, and clinically meaningful test endpoints.
It is a surface treatment designed to reduce interactions that can contribute to thrombus formation, such as protein adsorption, platelet adhesion, and coagulation activation.
No. PC is generally used as a biomimetic, hydration-based surface strategy, while heparin provides anticoagulant activity through a different mechanism.
Typical considerations include coating integrity, adhesion, durability, sterilization compatibility, simulated-use performance, and appropriate hemocompatibility endpoints for the finished device.
Zhang M, Pauls JP, Bartnikowski N, et al. Anti-thrombogenic surface coatings for extracorporeal membrane oxygenation: A narrative review. ACS Biomaterials Science & Engineering. 2021;7:4402–4419.
Böning A, Scheewe J, Ivers T, et al. Phosphorylcholine or heparin coating for pediatric extracorporeal circulation causes similar biologic effects in neonates and infants. Journal of Thoracic and Cardiovascular Surgery. 2004;127(5):1458–1465.
Henkes H, Bhogal P, Aguilar Pérez M, et al. Anti-thrombogenic coatings for devices in neurointerventional surgery: Case report and review of the literature. Interventional Neuroradiology. 2019;25(6):619–627.



